

Home / Specialties / TMS Billing Services for Psychiatry & Behavioral Health Practices
TMS Billing Services for Psychiatry & Behavioral Health Practices
Medivantek manages the billing side of transcranial magnetic stimulation for TMS clinics, psychiatry groups, and behavioral health practices across the United States. We verify TMS benefits before the mapping session, track every prior authorization against the treatment schedule, code 90867, 90868, and 90869 from the session record, and work denials until each claim is paid, corrected, or closed with a documented reason. You get one billing team that understands how a TMS course actually runs, from first treatment through taper, and where payers stop paying. Start with a free TMS billing audit of your current claims, authorizations, and A/R.
- HIPAA-compliant workflows
- Medicare and commercial payers
- Nationwide, all 50 states
- Works in your existing EHR
Specialized TMS Medical Billing & Coding Services
A TMS course is not a string of unrelated office visits. It is one authorized treatment plan delivered over many sessions across several weeks, and every claim inside it depends on the same few facts: the approved session count, the authorization dates, the diagnosis on file, and the motor threshold record. When a general psychiatric billing workflow treats each session as a standalone claim, those facts drift apart, and the denials arrive weeks later in batches. Our TMS billing and coding services keep the course together from the first benefits check to the last taper session.
Insurance Eligibility and TMS Benefits Verification
Before the mapping session, we confirm active coverage, network status, deductible and coinsurance, and whether the plan routes behavioral health through a separate administrator. We also check that TMS is a covered benefit under that specific plan, since some employer plans exclude it outright. Your front desk gets a plain summary of what the patient will owe, so the financial conversation happens before treatment starts, not after the first statement.
Learn more about Insurance Eligibility and TMS Benefits VerificationTMS Prior Authorization and Treatment Session Tracking
We build the authorization request from your clinical record: diagnosis, current severity scores, medication trials with drug, dose, and duration, psychotherapy history, and the psychiatrist’s order. Once approved, we log the authorized session count, start and end dates, and any taper allowance, then compare scheduled treatments against that window every day. When missed appointments push a course long, we request an extension while the authorization is still active.
Learn more about TMS Prior Authorization and Treatment Session TrackingTMS Medical Coding and Claim Submission
Each date of service is coded from the treatment log, not the appointment calendar: 90867 for the initial mapping session, 90868 for routine treatment, and 90869 on a day the motor threshold was re-measured. Diagnosis codes carry over from the authorization, rendering and supervising provider details are matched to payer enrollment, and every claim is scrubbed for code combinations, units, and authorization numbers before submission.
Learn more about TMS Medical Coding and Claim SubmissionTMS Payment Posting and Reimbursement Reconciliation
We post ERAs and EOBs line by line and compare each paid session against your contracted rate. Short payments are flagged and worked, not written off as contractual adjustments. Patient balances are released only after the payer finishes adjudicating, which keeps statements accurate and cuts down on billing calls to your office.
TMS Denial Management, Appeals, and A/R Follow-Up
Every denial is sorted by root cause: authorization, medical necessity, coding, eligibility, or timely filing. Correctable claims are fixed and resubmitted. Medical necessity denials get an appeal built from the record, including rating scale scores and medication history, and we help coordinate a peer-to-peer review when the payer offers one. Aged TMS claims are worked by payer and dollar value so the largest balances are not left sitting.
Learn more about TMS Denial Management, Appeals, and A/R Follow-UpTMS Provider Credentialing and Payer Enrollment
TMS claims fail quietly when the ordering psychiatrist, the supervising physician, or the treatment location is not enrolled correctly with a payer. We handle individual and group enrollment, NPI and tax ID alignment, CAQH upkeep, and revalidation dates, and confirm that each payer recognizes the site where TMS is delivered. Credentialing support is available with full-service TMS billing and can also be set up as a standalone engagement.
Learn more about TMS Provider Credentialing and Payer EnrollmentTMS Billing CPT Codes: 90867, 90868, and 90869
Three CPT codes cover therapeutic repetitive TMS. They look simple. Most TMS coding denials come from how the three codes interact within the same course and on the same date of service.
| CPT code | What it reports | How often | Billing rule to watch |
|---|---|---|---|
| 90867 | Initial treatment, including cortical mapping, motor threshold determination, delivery, and management | Once per course of treatment | Not reported with 90868 or 90869 |
| 90868 | Subsequent treatment delivery and management | Per session | Session count must match the authorization and the treatment log |
| 90869 | Subsequent motor threshold re-determination with delivery and management | When the threshold is re-determined | Reported instead of 90868 on that date, not alongside it |
CPT 90867: Initial TMS Treatment and Motor Threshold Determination
Reported for the first treatment of a course, when the clinician maps the treatment site, establishes the motor threshold, and delivers the first session. It is reported once per course. When a patient returns for a retreatment course, we confirm the payer recognizes it as a new course with its own authorization before billing 90867 again.
CPT 90868: Subsequent TMS Treatment Sessions
Reported for each standard treatment session after the first. The treatment log should show the date, the stimulation parameters, and the supervising physician for every session, so the number of claims matches the record line for line and holds up if the payer requests records.
CPT 90869: Motor Threshold Re-determination
Reported when the motor threshold is measured again during a course, for example after a medication change or when the clinician judges the original threshold no longer accurate. Because 90869 already includes that day’s treatment delivery, billing 90868 for the same date triggers a bundling edit and one of the two lines will deny. The reason for re-measurement belongs in the session note.

TMS Insurance Coverage, Medical Necessity & Prior Authorization
TMS coverage is decided policy by policy. Two patients with the same diagnosis and the same psychiatrist can get different answers because their plans follow different medical policies, and Medicare coverage depends on which contractor processes your claims. Most TMS revenue is won or lost here, before the first claim is ever filed.

Medicare TMS Billing Requirements
Medicare has no national coverage determination for TMS. Coverage comes from the Local Coverage Determination (LCD) published by your Medicare Administrative Contractor (MAC), and the criteria differ by jurisdiction. As one example, Noridian’s TMS policy (L37086), which covers California, Nevada, Hawaii, Alaska, Arizona, and other Western states, requires:
- A confirmed diagnosis of severe major depressive disorder, single or recurrent episode, in an adult
- Documented resistance or intolerance to antidepressant medication
- A trial of evidence-based psychotherapy without significant improvement, measured on a standardized scale
- An order from a psychiatrist who examined the patient, with treatment given under that physician’s direct supervision
Noridian’s billing article supports up to 20 sessions over four weeks plus taper, with 10 more sessions when the patient shows at least 25% improvement, and treats maintenance TMS as non-covered. We read the policy for your MAC before the first Medicare patient is scheduled and build the authorization file around it.

Commercial Insurance Coverage for TMS Therapy
Commercial plans write their own TMS medical policies, and they revise them often. Common requirements include a minimum number of failed antidepressant trials in the current episode, a baseline score on a scale such as the PHQ-9 or HAM-D, documented psychotherapy, and an age range. Some plans cover TMS for obsessive-compulsive disorder or adolescent depression; many do not. State Medicaid programs and their managed care plans set their own rules, and some exclude TMS entirely. We keep policy notes for every plan your patients carry and check the current version at the time of each authorization request.
ICD-10-CM Diagnosis Codes and Medical Necessity
The diagnosis on the claim has to match the diagnosis on the authorization and in the psychiatrist’s note. A correct code alone does not establish coverage; the record behind it does.
| ICD-10-CM | Description | Coverage context |
|---|---|---|
| F32.2 | Major depressive disorder, single episode, severe without psychotic features | Listed as supporting medical necessity in Noridian billing article A57692 |
| F33.2 | Major depressive disorder, recurrent, severe without psychotic features | Listed as supporting medical necessity in Noridian billing article A57692 |
| F42 series | Obsessive-compulsive disorder | Commercial plans only, where the policy covers OCD; not covered under Noridian’s Medicare LCD |

Clinical Documentation Required for TMS Claims
Payers and auditors look for the same core records. We review these before an authorization request and again before an appeal:
- Psychiatric evaluation confirming the diagnosis and episode severity
- Medication trial history with drug name, dose, duration, and response or side effects
- Psychotherapy history and outcome
- Baseline and follow-up scores on a validated scale such as PHQ-9, HAM-D, BDI, or MADRS
- Contraindication screening, including seizure history and implanted devices
- The psychiatrist’s order for treatment or retreatment
- Motor threshold records and daily session logs with dates, parameters, and supervising physician
Our TMS Revenue Cycle Management Process
Onboarding is built so your clinic keeps treating patients while billing changes hands. Most practices complete the transition in 30 to 45 days, depending on claim volume and system access.
Practice assessment and onboarding.
We review your payer mix, TMS volume, billing system access, open authorizations, and outstanding claims, then agree on a transition date.
Eligibility and authorization review.
Every active patient’s coverage and authorization is checked, and session tracking is set up for each open course.
Coding and documentation validation.
Session logs, diagnosis codes, and provider details are matched to the coding and payer rules that apply to each claim.
Claim submission and tracking.
Clean claims go out electronically and are monitored through acceptance and adjudication, with rejections fixed the same week.
Payment posting and denial resolution.
Remittances are reconciled line by line, and unpaid or denied sessions are corrected, appealed, or escalated.
Reporting and revenue cycle review.
You receive monthly reporting and a standing review call to go over trends, open issues, and expiring authorizations.

Why Choose Medivantek for TMS Billing Services?
Plenty of billing companies list TMS on their specialty page. The difference shows up in how they handle the course, the policy, and the follow-up.
Billing built around the treatment course.
Authorizations, session counts, and claims are tracked together for each patient, not as separate tasks.
Behavioral health billing depth.
Our team already bills psychiatry, mental health, substance use, and Spravato services, so TMS fits into the behavioral health workflows we already run every day.
Payer policy tracking.
We keep current notes on Medicare LCDs and commercial TMS policies for the plans your patients carry.
Works in your existing system.
We work inside your EHR and practice management software, including TherapyNotes, SimplePractice, AdvancedMD, Tebra, DrChrono, eClinicalWorks, NextGen, and others.
A named point of contact.
You work with an assigned account manager who knows your clinic, not a rotating queue, with a standing monthly review call.
HIPAA-compliant handling.
Access controls, secure file exchange, and documented procedures protect patient data at every step.
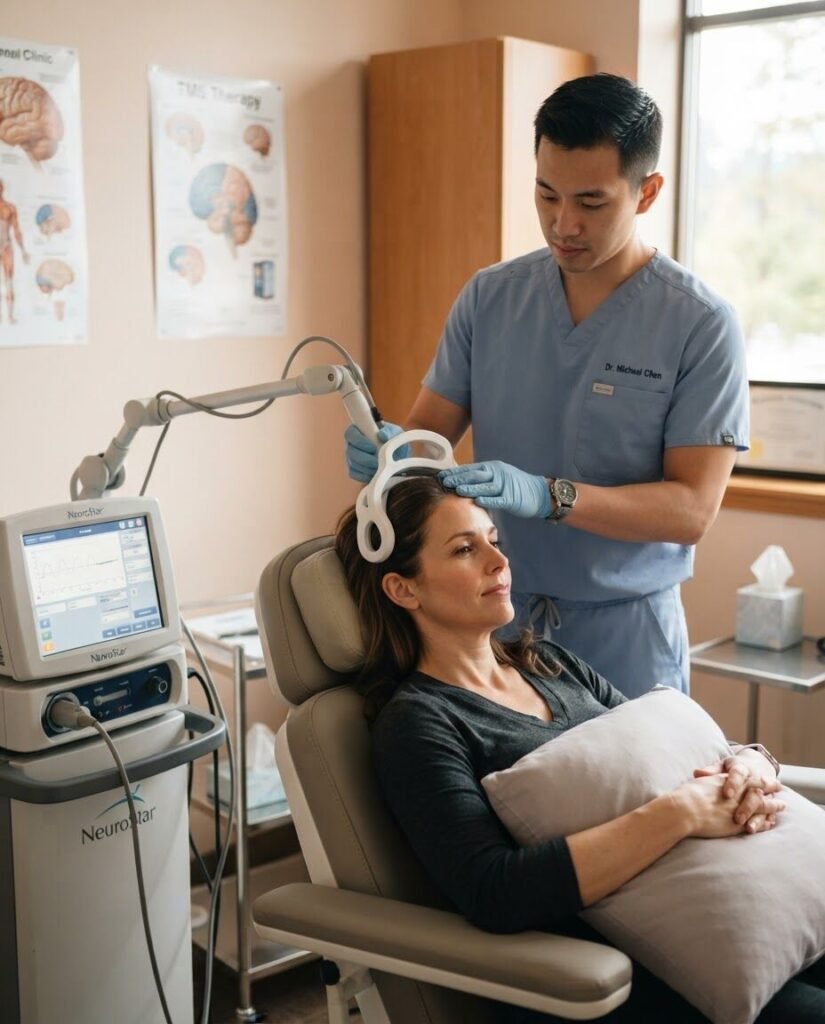
TMS Clinics and Healthcare Providers We Support
Clinics running one or two devices that need a full billing team without hiring one. We handle verification through collections so your staff can keep the treatment chair full.
Independent TMS Therapy Clinics
Groups offering TMS alongside psychiatric evaluations, medication management, psychotherapy, and Spravato. We bill TMS and the rest of your services in one workflow, with separate reporting for each service line. See our psychiatry billing services, mental health billing services, and Spravato billing services.
Psychiatry and Behavioral Health Group Practices
Several sites, several rendering providers, and different payer mixes by region. We standardize authorization tracking across every location and report results by site and by provider.
Practices Adding TMS Therapy Services
Clinics preparing for their first device. We help confirm which payers in your market cover TMS, complete enrollment for the supervising psychiatrist and treatment location, and set up billing before the first mapping session.

Provider Credentialing and Payer Enrollment
Credentialing and payer enrollment directly affect a psychiatric practice’s ability to participate in insurance networks and receive reimbursement. Medivantek helps providers manage enrollment and credentialing requirements alongside their billing operations.
- New payer enrollment
- CAQH profile setup and maintenance
- Re credentialing and revalidation tracking
- Medicare and Medicaid enrollment through PECOS
- Commercial payer panel applications
- Payer application status follow up
- Individual and group NPI alignment
- Taxonomy verification
A provider’s NPI, taxonomy, group information, and payer enrollment must align correctly. Errors can create claim rejections and payment delays. By connecting credentialing and billing, we help practices reduce administrative gaps that can affect the revenue cycle.
TMS Claim Readiness Checklist
We run every TMS course through this checklist. Use it to see where your current process holds up and where claims are slipping.
Before the First Treatment Session
- Active coverage and a TMS benefit confirmed for this specific plan
- Behavioral health carve-out identified, if the plan has one
- Supervising psychiatrist and treatment location enrolled with the payer
- Authorization approved, with session count and date range recorded
- Diagnosis on the authorization matches the psychiatrist’s note
- Baseline rating scale score documented
Before Each TMS Claim
- Date of service falls inside the authorization window
- Sessions billed to date are within the approved number
- CPT code matches the treatment log (90867, 90868, or 90869)
- Rendering and supervising provider details match payer enrollment
- Progress scores are current for the payer’s review interval
Common TMS Billing Challenges That Delay Reimbursement
TMS denials tend to repeat. Here are the four we see most, what causes them, and what we do about each one.
Missing or Expired TMS Prior Authorizations
- What happens
- Sessions delivered after the authorization end date, or beyond the approved count, deny as unauthorized and are often not appealable.
- Why it happens
- Missed appointments stretch the course past the authorized window, and nobody is comparing the schedule to the end date.
- How we handle it
- Daily comparison of scheduled sessions against each authorization, with extension requests sent while the authorization is still active.
Incorrect TMS CPT Codes and Session Documentation
- What happens
- 90868 billed on a 90869 date, 90867 billed twice in one course, or claim counts that do not match the treatment log.
- Why it happens
- Charges are entered from the appointment calendar instead of the clinical session record.
- How we handle it
- Charges built from the session log and reconciled to the authorization count before any claim is submitted.
Medical Necessity and Diagnosis-Related Denials
- What happens
- The payer denies after review or sends a records request mid-course.
- Why it happens
- Unspecified or moderate depression codes, incomplete medication trial details, or no baseline scale score.
- How we handle it
- Documentation review against the payer's policy before the authorization request, and appeal packets assembled from the record when a denial does occur.
TMS Claim Denials, Underpayments, and Aging A/R
- What happens
- Paid amounts fall below contract, small balances go unworked, and claims age past timely filing.
- Why it happens
- High-volume, per-session claims make short payments easy to miss.
- How we handle it
- Line-level payment variance review and A/R worked by payer and aging bucket every week.
What Your Monthly TMS Billing Report Includes
- Sessions delivered versus sessions authorized, by patient
- Authorizations expiring in the next 14 days
- Claims submitted, paid, pending, and denied
- Denials grouped by root cause and payer
- A/R aging by payer
- Underpayments identified and amounts recovered
A sample report is available on request during your free billing audit.

TMS Billing Services Pricing
We do not publish a flat rate, because two TMS clinics with the same number of devices can need very different levels of support. Your quote follows a free billing audit of your practice. In line with standard practice for specialty billing, our fee is typically set as a percentage of net collections, so it moves with what your clinic actually collects. There are no setup fees and no charge for the audit.

What Determines the Cost of Outsourcing TMS Billing?
- Monthly TMS treatment and claim volume
- Number of rendering providers and treatment locations
- Payer mix, including Medicare, Medicaid, and commercial plans
- Scope of services, from coding only to full revenue cycle management
- Prior authorization and credentialing needs
- Existing denials or aged A/R to clean up
- EHR and practice management system requirements

Request A Customized TMS Billing Proposal
Start with a free billing audit. Send us a recent month of TMS activity and your payer list, and we will come back with a written proposal that shows the scope, the price, and what changes in your first 90 days.
Frequently Asked Questions (FAQs)
What CPT codes are used for TMS billing?
Three CPT codes cover therapeutic repetitive TMS. Each date of service is coded from the treatment log, not the appointment calendar: 90867 for the initial mapping session, 90868 for routine treatment, and 90869 on a day the motor threshold was re-measured.
Can 90868 and 90869 be billed on the same date of service?
Because 90869 already includes that day’s treatment delivery, billing 90868 for the same date triggers a bundling edit and one of the two lines will deny. The reason for re-measurement belongs in the session note.
Does Medicare cover TMS therapy?
Medicare has no national coverage determination for TMS. Coverage comes from the Local Coverage Determination (LCD) published by your Medicare Administrative Contractor (MAC), and the criteria differ by jurisdiction. We read the policy for your MAC before the first Medicare patient is scheduled and build the authorization file around it.
How do you manage TMS prior authorizations?
We build the authorization request from your clinical record: diagnosis, current severity scores, medication trials with drug, dose, and duration, psychotherapy history, and the psychiatrist’s order. Once approved, we log the authorized session count, start and end dates, and any taper allowance, then compare scheduled treatments against that window every day. When missed appointments push a course long, we request an extension while the authorization is still active.
Do you offer TMS provider credentialing?
We handle individual and group enrollment, NPI and tax ID alignment, CAQH upkeep, and revalidation dates, and confirm that each payer recognizes the site where TMS is delivered. Credentialing support is available with full-service TMS billing and can also be set up as a standalone engagement.
How long does it take to move TMS billing to Medivantek?
Onboarding is built so your clinic keeps treating patients while billing changes hands. Most practices complete the transition in 30 to 45 days, depending on claim volume and system access.
How much do TMS billing services cost?
We do not publish a flat rate, because two TMS clinics with the same number of devices can need very different levels of support. Your quote follows a free billing audit of your practice. In line with standard practice for specialty billing, our fee is typically set as a percentage of net collections, so it moves with what your clinic actually collects. There are no setup fees and no charge for the audit.
